
Choosing a treatment with your doctor
The same problem usually has more than one reasonable answer, and the best one depends on your life as well as your scan. This page helps you have that conversation.
There is rarely one right answer
A diagnosis is usually not followed by a single instruction but by several options with different trade-offs. Two people with near-identical scans can suit different treatments, because age, occupation, other conditions and what each wants to return to are not the same.
A systematic review of high-quality clinical practice guidelines for musculoskeletal pain distilled eleven recommendations they agree on. Two of them are to give patient-centred care and to offer good non-surgical care before considering surgery.
That means the decision is not something your doctor makes alone and then reports to you. It is made together.

The usual order
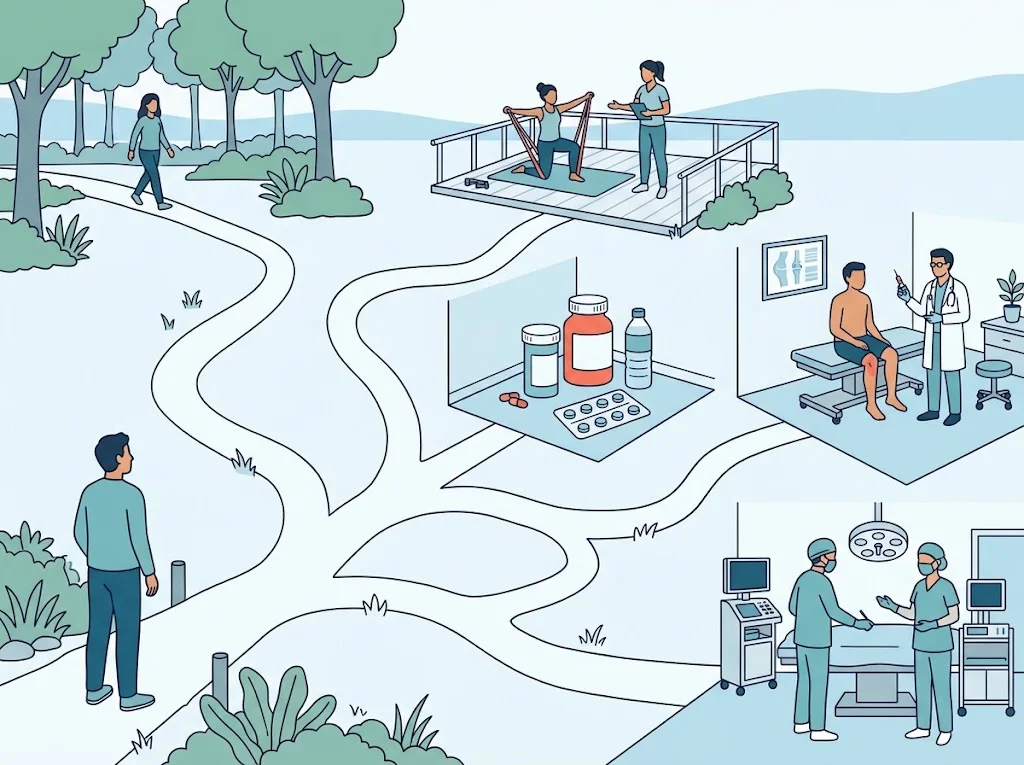
For most bone and joint problems, the options run from least to most invasive.
- Activity change and self-care — adjust what flares it, manage weight, start moving sensibly
- Rehabilitation and exercise — a programme that builds strength gradually, which is core treatment for many conditions rather than an optional extra
- Medicines — to let you move more, not to mask pain while you carry on overloading
- Injections — in some conditions, at some points
- Surgery — when the others are not enough, or when the condition clearly calls for it from the start
This is not a fixed sequence. Some injuries — a displaced fracture, an infected joint — need specific treatment immediately, not a ladder.
Questions that change the conversation
When surgery and non-surgical care come out level
In some conditions the research finds little between the two. A clear example is a degenerative meniscal tear. A systematic review of 10 randomised trials with 1,525 patients found that, in people without locking or catching, a proper physiotherapy programme gave results for pain and function comparable to arthroscopic surgery, and recommended starting non-surgically.
When outcomes are close, the deciding factors become the other things: the risks of an operation, the recovery time, the cost, and whether this is the right moment for you.
Things worth telling your doctor, even unasked
- What your job actually requires, and what you cannot do at the moment
- The activity you most want to get back to
- Every medicine and supplement you take, herbal ones included
- Other conditions, especially diabetes, kidney disease, heart disease and bleeding problems
- Whatever worries you most about treatment, even if it feels minor

Questions to ask your doctor
- What are all my options, including waiting?
- In my case, which do you recommend, and why?
- By when should I see a change, and what if I do not?
- If I wait another three months, what does that cost me?
- Can I take time to think and come back?
Frequently asked questions
Is it rude to ask a lot of questions?
Not at all. Understanding what is about to happen is part of good care. If there is not enough time in one appointment, ask for another, or ask whether there is something you can read.
Can I ask for a second opinion?
Yes, and it is normal for a big decision such as surgery. Asking does not imply distrust of the first doctor.
If I do not operate now, have I missed the chance?
It depends on the condition. Some genuinely have a window; others can wait with nothing lost. Ask directly: "if I wait three months, what does that cost me?"
References
- Lin I et al. What does best practice care for musculoskeletal pain look like? Eleven consistent recommendations from high-quality clinical practice guidelines: systematic review. Br J Sports Med. 2019
- Giuffrida A et al. Conservative vs. surgical approach for degenerative meniscal injuries: a systematic review of clinical evidence. Eur Rev Med Pharmacol Sci. 2020
Related conditions


Written by Assoc. Prof. Sorawut Thamyongkit, M.D.